Home
Appointment
Forms
Contact
Register Now
"
*
" indicates required fields
Step
1
of
2
50%
Are you an Intended Parent or a Egg Donor?
*
- Please Choose -
Intended Parent
Egg Donor
First Name
*
Last Name
*
Email / Username
*
Password
*
Enter Password
Confirm Password
Phone
*
State/Region
*
Country
*
Reproductive Physician
*
Willing to travel?
*
Yes
No
Maybe
How Did You Hear About Us?
*
Terms and Conditions
*
I agree to the terms and conditions
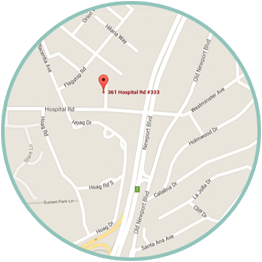
361 Hospital Road, Suite 333
Newport Beach, CA 92663
Call Us Today
949.494.6511